Patient Intake Form
Collect essential patient information before their first visit
8 fieldsconversationalHealthcare
Fields included
Full name*
Short textDate of birth*
DateEmail address*
EmailPhone number*
PhoneHome address*
AddressInsurance provider*
DropdownList any current medications and dosages
Long textList any known allergies (medications, food, environmental)
Long textLive Preview
Patient Intake Form
Collect essential patient information before their first visit
press Enter ↵

More Healthcare templates
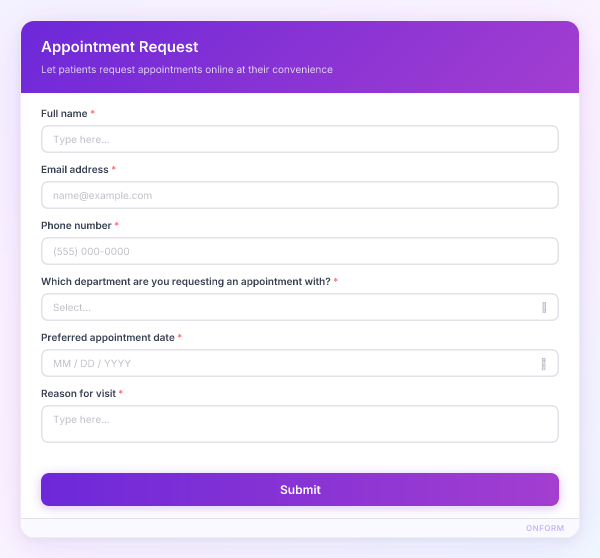
Appointment Request
Let patients request appointments online at their convenience
6 fieldsHealthcare
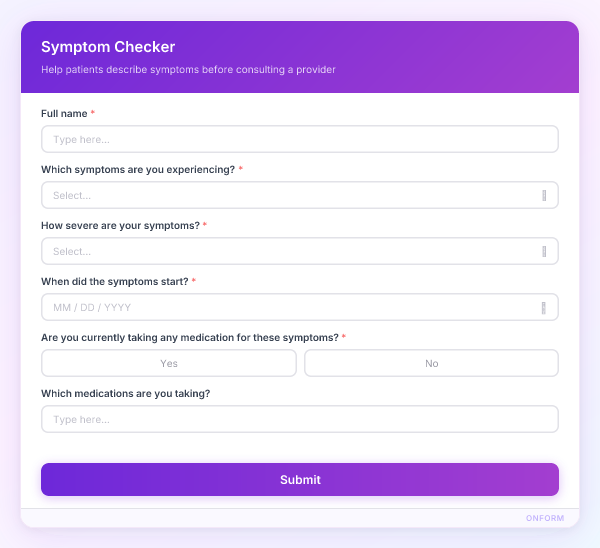
Symptom Checker
Help patients describe symptoms before consulting a provider
6 fieldsconversationalHealthcare
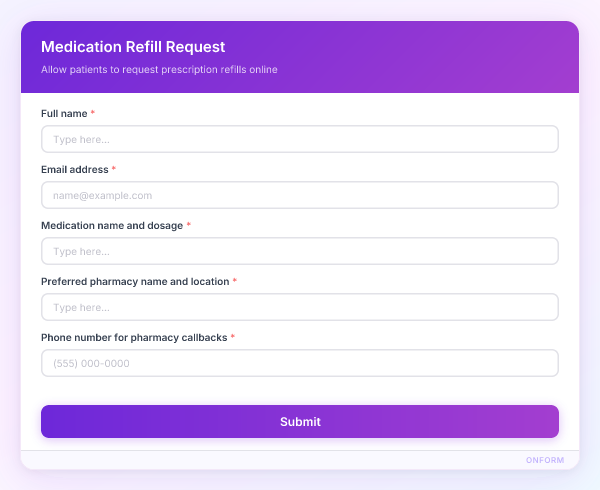
Medication Refill Request
Allow patients to request prescription refills online
5 fieldsHealthcare