Medication Refill Request
Allow patients to request prescription refills online
5 fieldsconversationalHealthcare
Fields included
Full name*
Short textEmail address*
EmailMedication name and dosage*
Short textPreferred pharmacy name and location*
Short textPhone number for pharmacy callbacks*
PhoneLive Preview
Medication Refill Request
Allow patients to request prescription refills online
press Enter ↵

More Healthcare templates
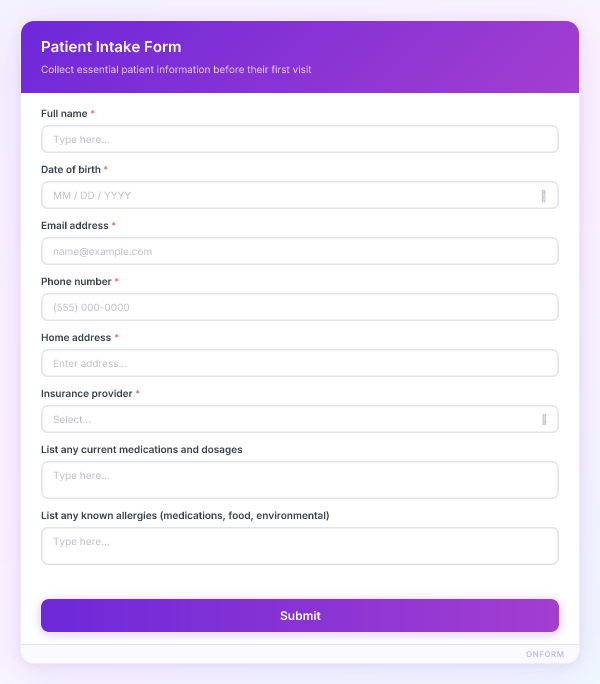
Patient Intake Form
Collect essential patient information before their first visit
8 fieldsHealthcare
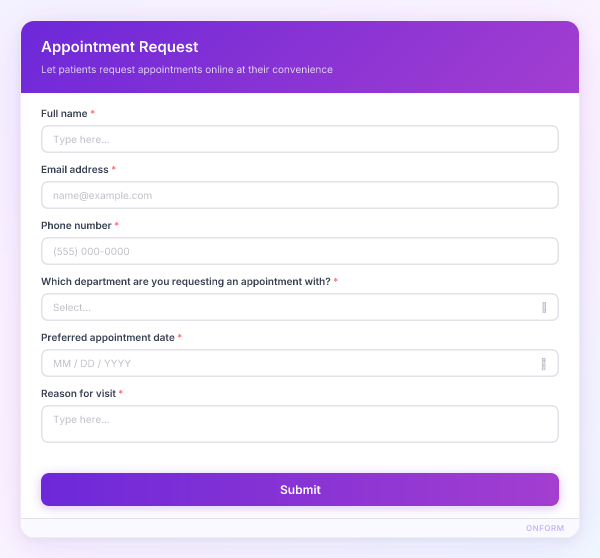
Appointment Request
Let patients request appointments online at their convenience
6 fieldsHealthcare
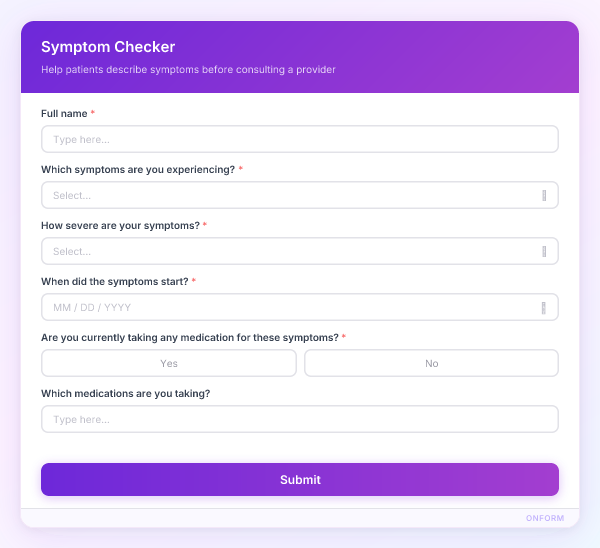
Symptom Checker
Help patients describe symptoms before consulting a provider
6 fieldsconversationalHealthcare